

Renal Sciences
Understanding Chronic Kidney Disease: Stages, Symptoms & When Dialysis Becomes Necessary
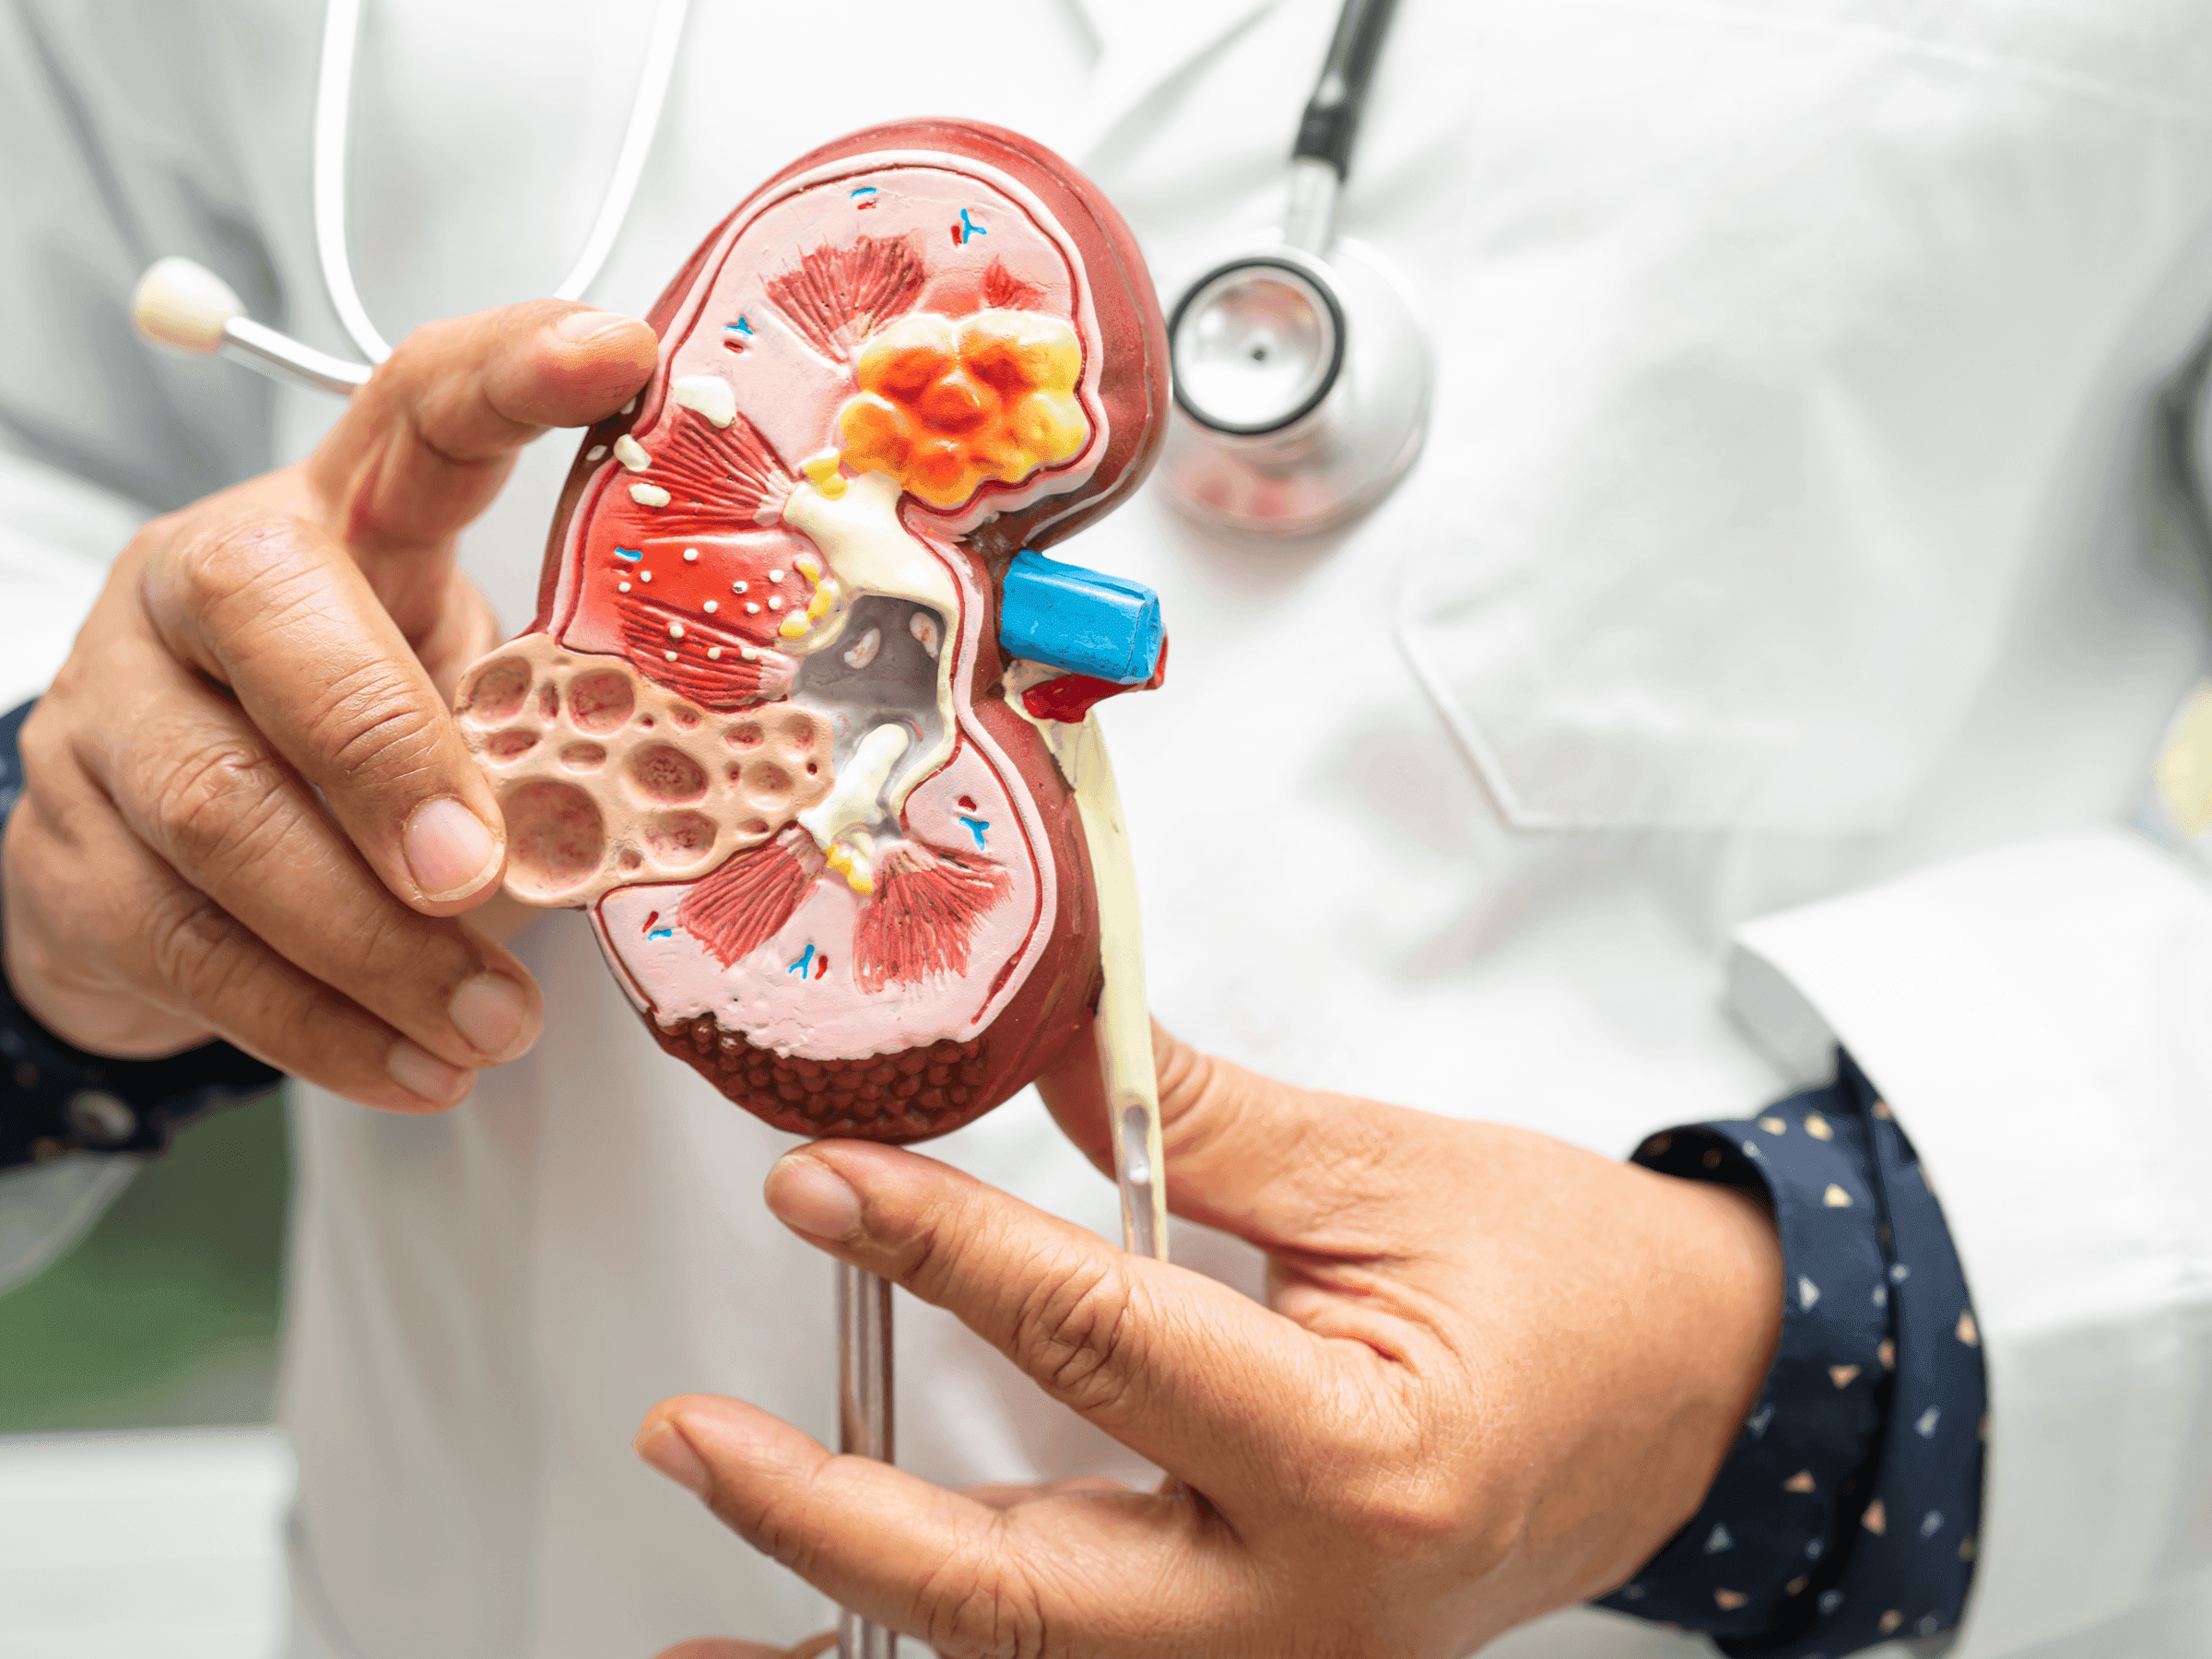
You opened the blood report to check one number. Now you have several new terms to worry about: creatinine, eGFR, stage three.
Before the family group starts recommending litres of water, special juices or a complete ban on dal, pause. A kidney report needs context. One abnormal result doesn't automatically mean chronic kidney disease, & a diagnosis doesn't automatically mean dialysis.
Chronic kidney disease (CKD) means that kidney damage or reduced kidney function has been present for at least three months. Understanding the cause, the pattern over time & your other health conditions helps the doctor decide what needs attention now & what can be planned ahead.
What Your Kidneys Do
Your kidneys remove waste & extra fluid from the blood. They also help balance salts & minerals, regulate blood pressure & support red blood cell production & bone health.
When they aren't working well, more than urine production can be affected. Blood pressure may rise, fluid may collect, or blood tests may show changes in potassium & other substances.
You can still pass urine with significant kidney disease. The amount of urine alone doesn't show how well the kidneys are clearing waste, & normal-looking urine can't rule out early disease.
Why Chronic Kidney Disease Develops
Diabetes & high blood pressure are common causes. Other possibilities include inflammation in the kidneys, inherited conditions, problems with urine drainage & kidney damage from some medicines.
The cause matters because treatments differ. Two people with the same kidney function estimate may have different outlooks & need different investigations.
Tell your doctor about diabetes, blood pressure, previous kidney injuries, repeated urine problems, stones & kidney disease in relatives. Include medicines bought without prescriptions, supplements & herbal preparations. A product being called natural doesn't mean it's suitable for your kidneys.
Chronic Disease & Sudden Kidney Injury Are Different
Kidney function can worsen suddenly during illnesses such as severe dehydration or infection, or because of certain medicines or a blockage. This is called acute kidney injury.
It can happen with or without existing CKD. The doctor uses your history, examination & earlier results to tell a recent change from a long-standing problem.
Don't read the three-month definition as a reason to wait three months for medical advice. A new abnormal result, particularly with illness or reduced urine, may need prompt assessment.
The Two Tests That Help Build the Picture
The Blood Test: eGFR
A blood test measures creatinine, a waste product from normal muscle activity. The result is combined with other information to estimate how well the kidneys filter, reported as the estimated glomerular filtration rate (eGFR).
This estimate is useful, but it is not a direct percentage of kidney function.
Muscle mass & other factors can affect creatinine-based estimates. In some situations, another blood marker called cystatin C, or other tests, may give a clearer picture. Your doctor decides whether that's needed.
The Urine Test: Albumin
Albumin is a protein that normally stays mainly in the blood. Increased leakage into urine can be a sign of kidney damage.
The urine albumin-to-creatinine ratio (UACR) measures this leakage relative to urine creatinine. It provides information that the blood test alone may miss.
Ask whether both tests have been done. Someone can have a reasonably good eGFR but ongoing albumin leakage that still needs attention. Abnormal urine results may need repeating because temporary factors can affect them.
Understanding the Stages of Chronic Kidney Disease
Doctors describe CKD using its cause, filtering level & amount of albumin in the urine. The stage is useful, but it's only part of the assessment.
The filtering categories below use eGFR measured in mL/min/1.73 m². You don't need to memorise the unit, but keep it with the number when you discuss your report.
| Category | eGFR | What it describes |
|---|---|---|
| G1 | 90 or above | Normal or high filtering estimate |
| G2 | 60 to 89 | Mildly reduced filtering estimate |
| G3a | 45 to 59 | Mild to moderate reduction |
| G3b | 30 to 44 | Moderate to severe reduction |
| G4 | 15 to 29 | Severe reduction |
| G5 | Below 15 | Kidney failure category |
G1 & G2 don't point to CKD unless there is another sign of kidney damage. In any category, a long-term problem has to be confirmed, not assumed from one test.
Albumin leakage is also grouped into categories: A1 is below 30 mg/g, A2 is 30 to 300 mg/g, & A3 is above 300 mg/g. Laboratories may use different units, so ask for help rather than comparing unlike numbers.
Higher albumin leakage can signal greater risk even when eGFR looks reassuring. The trend, underlying cause & your overall health guide monitoring & treatment.
Does Everyone Move Through All Five Stages?
No. CKD doesn't progress at the same speed in everyone. Some people stay stable for long periods; others have a greater risk of getting worse.
The doctor considers repeated results, albumin leakage, blood pressure, diabetes & the cause of disease. In appropriate patients, a validated risk calculator can help estimate the chance of needing kidney replacement treatment.
That estimate supports planning. It isn't a prediction of an exact date, & a single small change shouldn't be read without its medical context.
Symptoms: Why Feeling Well Is Not Enough
Early CKD often has no obvious symptoms. So testing matters for people at risk, including those with diabetes, high blood pressure, heart disease or a family history of kidney failure.
As disease advances, symptoms can include tiredness, poor appetite, nausea, itching, swelling, breathlessness or changes in urination. These can have other causes too, which is why examination & testing matter.
Don't wait for kidney pain. CKD doesn't need to cause pain to matter. If your doctor recommends monitoring because of diabetes or blood pressure, the purpose is to spot changes before symptoms become obvious.
What Treatment Tries to Achieve
Treatment aims to address the cause, slow further loss of function where possible, lower heart-related risk & manage complications. It also helps you plan ahead if the disease is more advanced.
An early nephrology assessment may be suitable depending on the findings, cause & risk. Your doctor can explain whether you need a specialist review now & how follow-up should be shared.
Blood Pressure, Diabetes & Kidney-protective Medicines
Keeping blood pressure & diabetes well controlled is central to care. Targets should be agreed with you individually, taking your health & treatment risks into account.
Some blood pressure medicines also reduce albumin leakage & protect kidney function in suitable patients. Another group, called SGLT2 inhibitors, can benefit some people with CKD, including some without diabetes.
These medicines need to be chosen & monitored by a doctor. Don't start them because a relative with kidney disease takes them. Equally, don't stop a prescribed medicine because a report changes slightly without discussing what the change means.
Ask when blood tests are due after medicine changes & what to do if you develop vomiting, diarrhoea or can't eat & drink normally. A written illness plan is more useful than guessing which tablet to skip.
Other Problems That May Need Attention
The team may check for a low red blood cell count (anaemia), abnormal mineral balance, acid build-up, poor nutrition or excess fluid. Treatment depends on the problem & its severity.
Heart health matters too. CKD is linked to heart & blood vessel (cardiovascular) risk, so blood pressure, cholesterol, smoking & other factors may be reviewed alongside the kidney results.
This can mean care from more than one professional, so keep an up-to-date medicine list for everyone treating you.
Food & Fluids: Avoid the Universal Kidney Diet
"Should I stop eating everything I enjoy?" is a reasonable question. The answer should come from your results & nutritional needs, not a list forwarded to everyone with CKD.
Reducing excess salt often helps blood pressure & fluid management. Packaged snacks, pickles, sauces & restaurant food can add a lot. Ask about a suitable target & practical swaps for the meals you already eat.
Protein needs depend on disease stage, nutrition & whether you receive dialysis. Cutting protein too far can cause harm. Dialysis can change requirements, so an old diet chart may no longer fit.
Potassium & phosphorus advice also depends on blood levels & treatment. Don't automatically cut out all fruit, vegetables or pulses. A kidney dietitian can help you choose well without needlessly narrowing your diet.
Nor should everyone force extra water or restrict fluids. The right amount depends on urine output, swelling, heart health & other factors. Ask for a clear daily plan if a limit is needed, including whether soups & other drinks count.
If diabetes or blood pressure also needs attention, internal medicine care can support management alongside your kidney specialist.
Be Careful With Everyday Medicines
Common anti-inflammatory painkillers, including ibuprofen & naproxen, can harm kidneys, particularly during dehydration or in people already at risk. Some cold & pain products contain the same ingredients.
Check with a doctor before using them. Mention CKD whenever a new medicine, supplement or imaging test is being considered. Some medicines need dose adjustments as kidney function changes.
This isn't a reason to refuse every test or stop all treatment. The team can weigh benefits, risks & alternatives with your kidney function in mind.
When Does Dialysis Become Necessary?
Dialysis removes waste & excess fluid when the kidneys can't do enough of that work. The decision to start is based on symptoms, examination, blood results, fluid balance, quality of life & your preferences.
It isn't triggered by one creatinine value or by the stage number alone. KDIGO guidance notes that the need often arises when eGFR is between 5 & 10, but not always. Some people need treatment sooner because of complications.
Reasons can include dangerous potassium or acid levels that medicines can't control, excess fluid that can't be managed, or symptoms from waste build-up. Worsening nutrition despite proper care may also contribute.
Planning should begin before a crisis if risk is high. A discussion about dialysis access or transplantation doesn't necessarily mean dialysis starts that week. It gives time to understand options & prepare safely.
Haemodialysis
Haemodialysis filters blood through a machine outside the body & returns it to you. It needs suitable access to the bloodstream, planned with the team where possible.
The schedule depends on your needs & the treatment setting. Ask about transport, work, recovery after sessions & access care. These practical questions are part of choosing treatment, not distractions.
Peritoneal Dialysis
Peritoneal dialysis uses the lining inside the abdomen as a filter. Dialysis fluid is introduced & drained through a soft tube, with training & a planned routine.
It can be performed at home in suitable circumstances. Discuss the space, hygiene, supplies, assistance & follow-up required. The choice depends on medical suitability & what can be managed safely in everyday life.
Transplantation & Conservative Care
A kidney transplant may be an option for eligible people, sometimes before dialysis begins. Assessment covers medical suitability & donor-related matters. You'll need ongoing medicines & follow-up after a transplant.
Conservative kidney care is another planned approach for people who choose not to have dialysis or a transplant after an informed discussion. It focuses on symptoms, comfort & quality of life. It doesn't mean that medical care stops.
Discuss the likely benefits & burdens of each option in your circumstances, alongside your goals, other illnesses & available support.
When to Seek Urgent Medical Help
Severe breathlessness, chest pain, new confusion, marked drowsiness or seizures need emergency assessment. A major reduction in urine, especially with swelling or illness, also needs prompt medical attention.
If your care team contacts you about a dangerously abnormal blood result, follow their instructions immediately even if you feel well. Some serious blood chemistry changes give no reliable early warning.
Questions to Take to Your Next Visit
Ask what caused the kidney problem, whether chronic disease is confirmed, & what your eGFR & urine albumin results show together. Bring older reports to show the trend.
Find out when to repeat tests, which medicines need monitoring & whether diet or fluid advice has changed. If the disease is advanced, ask when planning should begin & who can explain the options.
Write the agreed next step down. A useful consultation should leave you with more than a stage number.
Make Room for Everyday Life in the Care Plan
Kidney care has to fit around meals, work, travel & the people who support you. Tell the team if a recommendation is difficult to follow. A food plan needs to work with your household's cooking, your budget & your appetite, not just a list of nutrients.
If several relatives are helping, agree on one current medicine list & one place for reports. Keep dates visible, so it's easier to tell an old prescription from the current plan & show the doctor what changed between visits.
Ask which measurements, if any, you should record at home. Some people may be asked to monitor blood pressure or weight. Follow your own instructions rather than collecting numbers without knowing when to report them.
If dialysis is being discussed, bring practical questions early. Who will explain the choices again? What training is needed? How will treatment affect travel to work or support at home? Which problems should prompt an immediate call?
It's also reasonable to ask for an explanation in your preferred language & to repeat the plan back in your own words. Knowing what to do next matters more than understanding a medical term.
Keep asking questions. A family member can help take notes if you wish, but your concerns & preferences should guide the conversation. Questions are easier to deal with when raised openly than when saved for the journey home.
Understand the Pattern, Not Just the Number
A kidney diagnosis brings understandable questions. Begin with the confirmed cause, repeat results & a clear care plan. Knowing what needs attention now, & what may need planning later, makes the next step easier.
Disclaimer: This article provides general health information & does not replace professional medical advice, diagnosis or treatment. Always consult a qualified doctor for medical advice, diagnosis & treatment. Do not ignore symptoms, delay seeking care or change prescribed treatment without consulting your doctor.
Frequently Asked Questions

Latest Blogs
View All BlogsLatest Blogs

General
World Mental Health Day: Breaking the Stigma Around Seeking Psychiatric & Neurological Care

Orthopaedics
World Arthritis Day: Early Signs, Diagnosis & Modern Treatment Options for Joint Pain

Internal Medicine
Seasonal Flu & Viral Infections: How to Protect Your Family This Festive Season
General
World Sight Day: Common Eye Conditions & the Importance of Regular Eye Check-ups
General
World Mental Health Day: Breaking the Stigma Around Seeking Psychiatric & Neurological Care
Orthopaedics
World Arthritis Day: Early Signs, Diagnosis & Modern Treatment Options for Joint Pain
Internal Medicine
Seasonal Flu & Viral Infections: How to Protect Your Family This Festive Season
General
World Sight Day: Common Eye Conditions & the Importance of Regular Eye Check-ups


